



Clascoterone clinical trials show a measurable benefit over vehicle for facial acne, but the size and meaning of that benefit depend on the endpoint. In the pivotal studies of clascoterone 1% cream, treatment success required both a substantial improvement in the investigator’s overall assessment and an assessment of clear or almost clear skin. Lesion-count endpoints captured a different outcome: how much inflammatory and noninflammatory acne changed from baseline.
These measures are complementary, not interchangeable. A participant could have a meaningful reduction in lesions without meeting the strict global success definition. Equally, a reported success rate alone does not show the number or types of lesions that remained.
What the pivotal trials measured
Two randomized, double-blind, vehicle-controlled phase 3 trials evaluated clascoterone cream, 1%, applied twice daily for 12 weeks in patients with facial acne vulgaris. The studies enrolled participants aged 9 years and older, with most participants aged 12 years or older. Their primary efficacy assessments combined an Investigator’s Global Assessment (IGA) success measure with absolute changes in inflammatory and noninflammatory lesion counts at week 12.
The comparison was against the cream vehicle rather than an established active acne treatment. This distinction matters: the trials estimate the contribution of clascoterone in the tested formulation and study conditions, but they do not establish whether it is more or less effective than a retinoid, benzoyl peroxide, an antibiotic or another hormonal treatment.
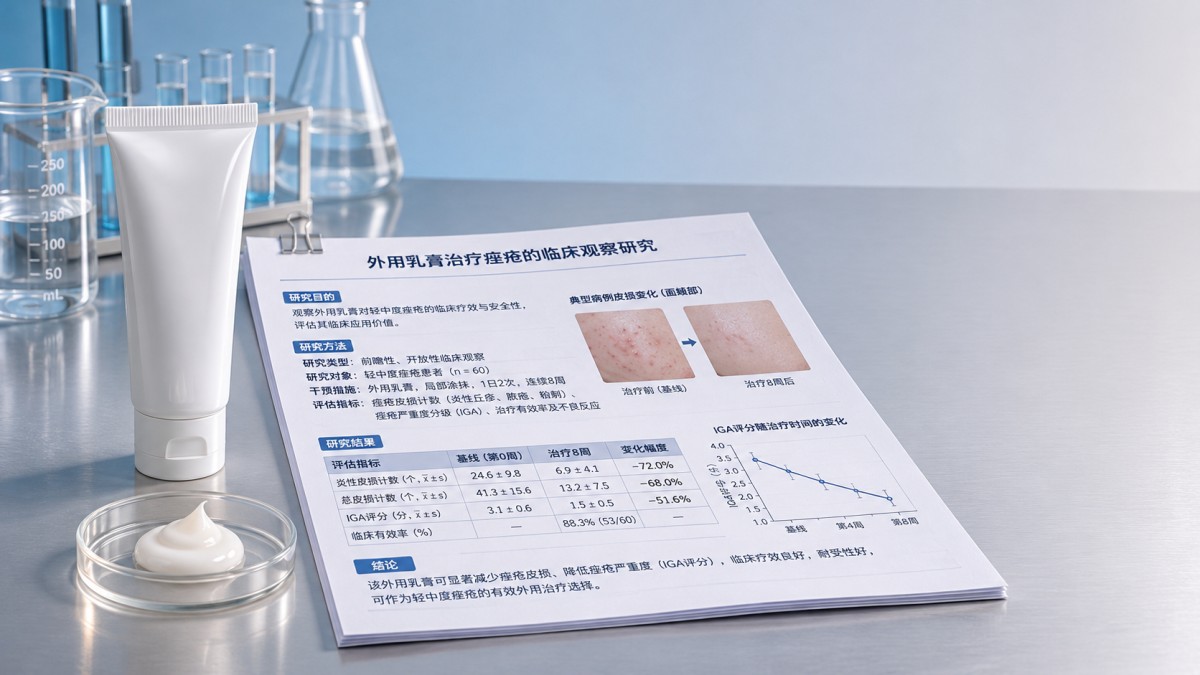
IGA success is a threshold, not an average improvement
IGA uses an investigator-rated scale to describe the overall severity of acne. In the pivotal clascoterone studies, treatment success at week 12 required an IGA score of 0 or 1—clear or almost clear—and at least a two-grade improvement from baseline. Both conditions had to be met.
This definition sets a relatively demanding endpoint. A patient who moved from severe to moderate acne could improve substantially without being counted as a success. A patient who reached an almost-clear score but improved by only one grade would also fall short of the specified success definition. The endpoint is therefore useful for identifying a defined, high level of response, but it should not be treated as the proportion of patients who experienced any benefit.
In the two phase 3 trials, week-12 IGA success was reported in approximately 18% and 20% of clascoterone-treated participants, compared with approximately 7% and 9% in the respective vehicle groups. These figures indicate an absolute difference of roughly 11 percentage points in each trial. They do not mean that only the participants classified as successes improved, nor do they describe durability after week 12.
The vehicle response is part of the interpretation. Changes in acne over time, study participation, application of the vehicle and other trial-related factors can contribute to improvement in the control group. Subtracting the vehicle response provides a more informative view of the observed treatment effect than the active-group success rate alone.
Lesion counts describe a different dimension of response
The trials assessed inflammatory lesions, such as papules and pustules, separately from noninflammatory lesions, such as open and closed comedones. This separation matters because the two lesion categories reflect different visible components of acne and need not change by the same amount in an individual patient.
An absolute change is the baseline count minus the count at the assessment visit. For example, a reduction from 30 inflammatory lesions to 18 is an absolute reduction of 12 lesions. A percentage change expresses the same reduction relative to baseline—in this example, 40%. Both are useful, but they answer different questions: absolute change shows the number of lesions removed, while percentage change accounts for the starting count.
Baseline severity can affect comparisons. A reduction of 10 lesions represents 50% for someone starting with 20 lesions but 25% for someone starting with 40. Conversely, two groups with the same percentage reduction can differ substantially in the number of lesions remaining. Baseline counts, final counts and the active-versus-vehicle difference should therefore be considered together.
Lesion counts also have measurement limits. Counting depends on identifying and classifying individual lesions consistently across visits. The definition of eligible lesions, anatomical area assessed, counting procedures and handling of missing visits can all influence the reported estimate. A numerical difference between studies is not automatically a difference in intrinsic drug activity.
How to read the endpoints together
IGA success and lesion-count reduction describe related but distinct outcomes. The global score summarizes the investigator’s assessment of overall severity; the count endpoints quantify changes in specific lesion categories. Neither should be used as a substitute for the other.
A credible efficacy assessment examines whether all three outcomes favor treatment over vehicle and whether the differences are large enough to matter for the intended use. Statistical significance helps assess compatibility with the null hypothesis under the prespecified analysis; it does not by itself establish that the observed difference is clinically meaningful for every patient.
Study population and timing limit the inference
The pivotal results apply most directly to facial acne in participants meeting the studies’ entry criteria. Baseline severity, lesion-count ranges and exclusions define who was represented. Results should not be assumed to apply unchanged to predominantly truncal acne, populations outside the studied age range, or patients with substantially different disease severity or concurrent treatments.
Week 12 is the principal comparison point for the pivotal efficacy endpoints. Earlier observations can help describe the trajectory of response, but an apparent early difference should be interpreted in light of the study’s statistical plan and uncertainty. A week-12 result also does not establish when an individual will respond or whether improvement will persist after treatment stops.
Longer-term exposure studies can contribute information about continued use and tolerability, but their design matters. An uncontrolled extension, for example, is less suitable than a randomized controlled comparison for estimating how much sustained improvement is attributable to clascoterone rather than other influences.
Mechanism supports the hypothesis, not the magnitude of efficacy
Clascoterone acts as an androgen receptor inhibitor in the skin. That mechanism provides a rationale for studying it in acne, but receptor activity alone cannot predict the clinical effect size, the proportion of patients who reach IGA success, or its comparative performance against other treatments. The vehicle-controlled lesion and global-assessment results provide the relevant clinical evidence for the tested cream.
The same boundary applies when reviewing other raw materials used in cosmetic or research formulations. A material such as S-Allyl-L-Cysteine should not be assigned clascoterone’s acne efficacy or androgen-receptor mechanism merely because both appear in skin-related ingredient discussions. Clinical findings are specific to the substance, formulation, population and regimen studied.
For a defensible assessment, retain the reported denominators, baseline characteristics, week-12 estimates and uncertainty measures alongside each endpoint. The central question is not whether a single headline percentage looks high or low, but how much additional improvement was observed over vehicle, in which lesions, under which conditions and with what limits on extrapolation.
Sources: Hebert A, et al. “Efficacy and Safety of Topical Clascoterone Cream, 1%, for Treatment in Patients With Facial Acne: Two Phase 3 Randomized Clinical Trials.” JAMA Dermatology, 2020;156(6):621–630. U.S. Food and Drug Administration, prescribing information for WINLEVI (clascoterone) cream, 1%.
News
- ▶ Pharma West Africa 2026
- ▶ Clascoterone Clinical Trials: What Acne Efficacy Endpoints Tell Us
- ▶ Clascoterone as a Cosmetic Raw Material: Is It Permitted in Skincare?
- ▶ Clascoterone Raw Material for Topical Drug Development: Impurity Control
- ▶ Glabridin Supplier Qualification: Checking Origin, Assay, and Traceability
Message
Chemical Engineering Field
24/7 before-sales and after-sales services
Comprehensive technical support