



Clascoterone side effects are best understood in the context of how clinical trials define, collect, and report safety outcomes. For technical evaluators, an adverse-event percentage is only the beginning: event severity, treatment duration, exposure conditions, and differences between active and control groups all shape the interpretation of tolerability. This article examines the measures used in clinical studies, with particular attention to local skin reactions, systemic findings, and the limits of trial evidence in pharmaceutical assessment.
Start with the product and the study population
Clascoterone is a topical androgen receptor inhibitor. Safety findings should be tied to the specific formulation, concentration, indication, and dosing regimen studied. Evidence for clascoterone cream used to treat acne, for example, should not automatically be transferred to a different formulation, application area, or investigational indication.
In the United States, the approved acne product is clascoterone cream 1%, indicated for topical treatment of acne vulgaris in patients 12 years of age and older. Its prescribing information is a useful starting point, but a technical assessment may also require the underlying study publications, clinical study reports where available, and the current label in the relevant jurisdiction.
Before comparing reported events, establish who entered the trial, how long they were treated, how much product they applied, and whether participants used other acne therapies. A trial involving a limited treatment area and selected participants may not predict every outcome in routine practice.
Adverse events and skin assessments are not the same measure
An adverse event is an unfavorable medical occurrence during a study; it is not automatically caused by the investigational product. A treatment-emergent adverse event is generally one that begins or worsens after treatment starts, according to the study’s definition. An adverse reaction, by contrast, implies that a causal relationship is at least reasonably possible under the applicable reporting framework.
Local skin reactions can be collected separately from spontaneously reported adverse events. Investigators may examine treated skin at scheduled visits and grade findings such as redness, scaling, or dryness, even if a participant does not report discomfort. Consequently, a skin-reaction table and an adverse-event table may describe overlapping observations using different methods and denominators. They should not be added together as though they represent distinct patients.
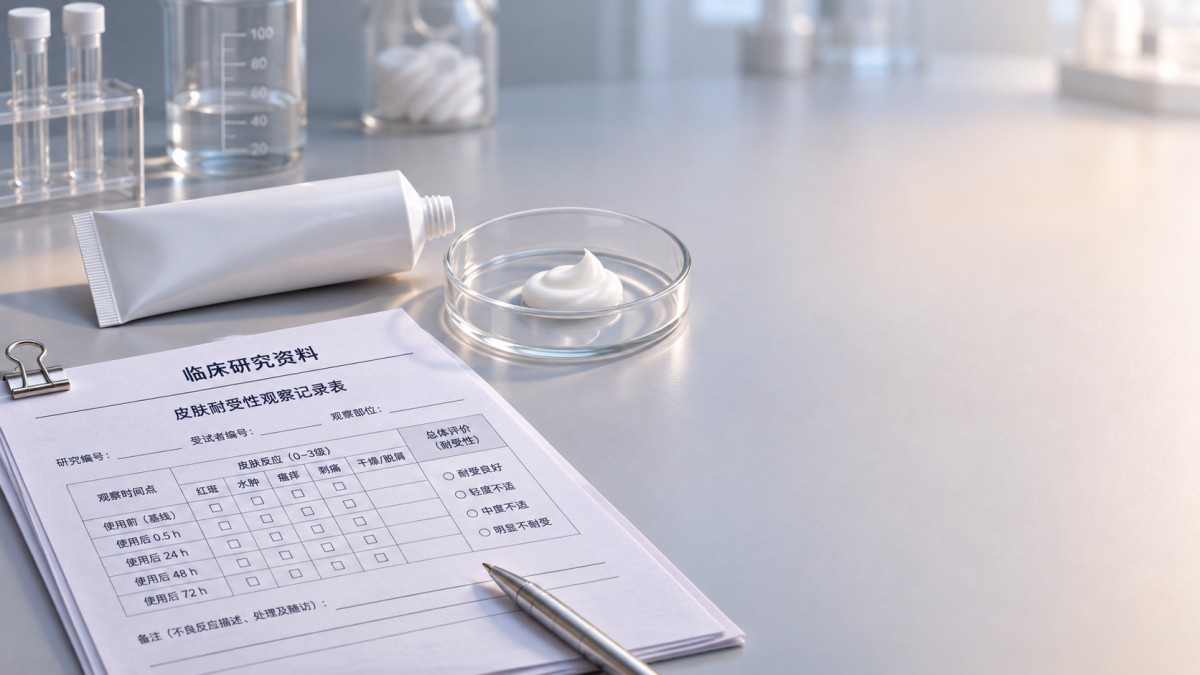
For each outcome, a reviewer should look for the following:
- Collection method: Was the finding solicited during a skin examination, reported by the participant, or identified through a laboratory test?
- Timing: Was it present at baseline, first observed during treatment, or still present after treatment ended?
- Severity and seriousness: Severity describes intensity; a serious adverse event is classified by regulatory criteria such as hospitalization or a life-threatening outcome. The terms are not interchangeable.
- Action and outcome: Did the event resolve, lead to dose interruption, require treatment, or cause discontinuation?
- Attribution: Did the investigator assess the event as related to treatment, and what evidence supported that assessment?
Reading local tolerability data in context
For a topical acne medicine, application-site findings are central to the assessment. The US prescribing information for clascoterone cream 1% describes local skin reactions observed in clinical studies, including erythema, scaling or dryness, and edema. These observations need to be read alongside baseline skin findings and the vehicle-control results: acne itself, skin-care practices, and the formulation vehicle can all affect the treated area.
A useful comparison asks not only how many participants had a reaction, but how many experienced a new or worsened finding after treatment began. Check the grading scale and whether the published table reports the maximum grade at any visit or the grade at a particular time point. A maximum-grade summary can be useful for detecting the worst observed reaction, but it does not reveal how long that reaction lasted.
Denominators matter as well. The number assessed at a later visit may be smaller than the randomized population because of missed visits or discontinuations. If the active and vehicle groups differ in follow-up, a simple percentage comparison may be misleading.
Why the vehicle group matters
A vehicle-controlled design helps distinguish effects associated with the active ingredient from those associated with the cream base and other aspects of trial participation. It does not eliminate uncertainty. The vehicle may itself influence tolerability, and a small difference between groups may be imprecise when events are uncommon. Review absolute counts, percentages, and, where available, confidence intervals rather than relying on a claim that one group had “more” or “fewer” events.
Systemic safety: exposure and biological effects
Although clascoterone is applied to the skin, topical administration does not rule out systemic absorption. The amount absorbed can depend on the formulation, dose, treatment area, skin condition, and duration of use. Pharmacokinetic studies and maximum-use studies therefore address a different question from a routine adverse-event listing: whether measurable systemic exposure occurs under the studied conditions.
One safety issue identified in US prescribing information is hypothalamic-pituitary-adrenal (HPA) axis suppression, evaluated in studies using adrenal function testing. The label also reports hyperkalemia in clinical studies. These findings should be interpreted with the study population, sampling schedule, laboratory thresholds, and follow-up in view. An abnormal test result is not automatically equivalent to a symptomatic clinical outcome, but neither should it be dismissed without reviewing its magnitude and clinical context.
For an evaluator, the questions are practical: How many participants were tested? Were results measured at baseline and after treatment? Were abnormal findings repeated or followed until resolution? Was the study designed to investigate a specific safety signal, or was the finding exploratory? The answers determine how much weight a laboratory result can carry.
A compact framework for comparing safety reports
When comparing studies, avoid treating different follow-up periods as equivalent. A 12-week incidence proportion and a longer-term cumulative proportion capture different opportunities for events to occur. Exposure-adjusted rates may help in some analyses, but only when their assumptions and calculation methods are appropriate and consistently applied.
What trial data cannot establish on their own
Clinical trials can characterize common events under controlled conditions, but their size and eligibility criteria limit detection of rare or delayed outcomes. People with significant comorbidities, pregnancy, extensive skin damage, or concurrent therapies may be underrepresented or excluded. Absence of a signal in such a population is not proof of absence of risk.
Open-label extension studies can add longer-term information, yet they usually lack the same concurrent control and may include participants who tolerated earlier treatment. Postmarketing surveillance can identify possible signals in broader use, although spontaneous reports generally cannot establish incidence or causality by themselves.
The assessment should therefore bring together the current prescribing information, controlled trials, extension data, and relevant regulatory updates. Any conclusion should state the formulation and population to which it applies, as well as the uncertainty that remains.
Separating clinical safety from raw-material quality
Technical teams evaluating pharmaceutical ingredients also need to keep clinical outcomes distinct from material specifications. Purity, impurity profiles, residual solvents, and microbial limits are important quality attributes, but a certificate of analysis for a raw material does not establish the safety of a finished topical formulation. Clinical tolerability depends on the complete product, its use conditions, and the evidence generated in patients.
The same distinction applies across Jinan Jianfeng Chemical’s ingredient portfolio. For example, its Coenzyme Q10 is presented as a nutraceutical ingredient, with supplied specifications covering assay, impurities, residual solvents, and microbiological limits. It is a separate material and is not evidence for the safety or efficacy of clascoterone.
A sound evaluation of clascoterone side effects ultimately rests on traceability: connect each finding to its population, formulation, collection method, and comparator. That discipline makes the difference between repeating a safety table and understanding what the trial actually measured.
News
- ▶ Pharma West Africa 2026
- ▶ Clascoterone Side Effects: What Clinical Trial Safety Data Measure
- ▶ Copper Peptides in Skincare: Choosing Formats for Serum Formulation
- ▶ NAD as an Energy Ingredient: Cellular Role vs. Supplement Evidence
- ▶ Water-Soluble Copper Peptides: Solubility Checks for Skincare Formulas
Message
Chemical Engineering Field
24/7 before-sales and after-sales services
Comprehensive technical support